


 ACCESS
Systematic Review
Volume 1, Article ID: 2026.0003

Fabrice Zobel Lekeumo Cheuyem
zobelcheuyem@gmail.com


Davy Roméo Takpando-Le-Grand
legrantak@yahoo.fr

Chabeja Achangwa
chabejaacha@yahoo.com

Lionel Berthold Keubou Boukeng
liokeu@yahoo.fr

Solange Dabou
solangedabs@gmail.com

Henri Donald Mutarambirwa
mutarahd2@gmail.com

Raissa Katy Noa Otsali
mballaotsalinoaraissakaty@gmail.com

Ariane Nouko
arianenouko@gmail.com

Michel Franck Edzamba
michel.medzamba@fmsb-uy1.cm


Martine Golda Mekouzou Tsafack
ptsafackgolda@yahoo.com

Armel Evouna Mbarga
evounarmel@gmail.com

Georges Nguefack-Tsague
nguefacktsague@gmail.com
1 Department of Public Health, Faculty of Medicine and Biomedical Sciences, The University of Yaoundé 1, Yaoundé, Cameroon
2 Field Coordinator of Frontline Field Epidemiology Training Program, Bangui, Central African Republic
3 Department of Public Health, Faculty of Medical Sciences, University of West Indies, Bridgetown, Barbados
4 Direction of Disease, Epidemics and Pandemics Control, Ministry of Public Health, Yaoundé, Cameroon
5 Department of Public Health and Social Sciences, Faculty of Medicine and Pharmaceutical Sciences of Sangmelima, University of Ebolowa, Ebolowa, Cameroon
6 Department of Biochemistry, University of Dschang, Dschang, Cameroon
7 Migration Health Assessment Center (MHAC), International Organization for Migration, Yaoundé, Cameroon
* Author to whom correspondence should be addressed
Received: 17 Oct 2025 Accepted: 17 Apr 2026 Available Online: 17 Apr 2026 Published: 20 May 2026
This study incorporated 12 years of evidence (2010–2022) on Mpox epidemiology, vaccination, and clinical patterns in the Central African Republic (CAR), providing insights to inform targeted control strategies for this re-emerging threat. This systematic review and meta-analysis were conducted in accordance with PRISMA guidelines. Literature searches were performed using PubMed, Scopus, ScienceDirect, Web of Science, Embase, the Cochrane Library, and AJOL. A random-effects model was used to pool estimates in R version 4.5.2. A p-value of <0.05 was considered statistically significant. A total of seven studies conducted between 1984 and 2023 were included in the analysis. The findings revealed a pooled severity rate of 60.92% (95% confidence interval [CI]: 47.54–72.83), with the highest estimate observed in Health Region 6 at 77.27% (95% CI: 55.64–90.21). Prior to the global Mpox outbreak in 2022, the case fatality rate (CFR) among confirmed cases was 10.71% (95% CI: 4.52–23.28). The Eastern Health Regions reported a higher CFR of 10.81% (95% CI: 4.03–25.93), whereas the Western Regions reported a CFR of 0.00% (95% CI: 0.00–100.00). Among suspected cases, the CFR was 12.13% (95% CI: 5.59–24.34), with a slight decrease to 9.09% (95% CI: 0.23–41.28) following 2022. This geographic disparity persisted, with higher rates observed in the Eastern Regions (9.95%; 95% CI: 3.39–22.71) compared with the Western Regions (5.26%; 95% CI: 0.74–29.39). Vaccination uptake in CAR was 20.00% (95% CI: 10.33–35.17). The clinical profile included fever (91.1%; 95% CI: 42.9–99.3), rash (85.5%; 95% CI: 75.7–91.8), and lymphadenopathy (57.0%; 95% CI: 34.3–77.1). The Central African Republic is among the African countries most affected by Mpox. The disease burden is characterized by high severity, elevated mortality, and suboptimal vaccine coverage, particularly in the eastern regions. To prevent future outbreaks in the country, these findings highlight the need to improve vaccine distribution, prioritize high-risk populations, and strengthen surveillance systems, including genomic sequencing capacity. Context-specific interventions, such as community education on preventive measures and healthcare worker training, may further contribute to reducing Mpox-related morbidity and mortality.
High disease burden in CAR: The study findings indicate that the Central African Republic exhibits a high pooled severity rate of 60.9% and a case fatality rate (CFR) of 10.7% among confirmed cases, which is substantially higher than the corresponding global estimates. Significant regional disparities: Health Region 6 recorded the highest severity rate (77.3%), while the eastern regions exhibited a higher mortality burden (case fatality rate [CFR]: 10.8%) compared with the western regions (0.0%). Vaccination gap: Outbreak response and prevention strategies were undermined by low Mpox vaccination uptake (20.0%) Clinical presentation: Fever (91.1%), rash (85.5%), and lymphadenopathy (57.0%) were the most commonly reported symptoms. This clinical profile is consistent with Clade I Mpox virus, which is known to circulate in the region. Contextualization of risk with conflict and zoonotic exposure: The sociopolitical context of the Central African Republic, including disruptions to healthcare services due to armed conflict, may have contributed to the elevated mortality observed. In addition, exposure associated with hunting practices and forest-based livelihoods increases the risk of disease transmission.
Mpox is an infectious viral disease caused by the monkeypox virus (MPXV) [1]. In 2022, the World Health Organization (WHO) declared Mpox a Public Health Emergency of International Concern; it was declared a PHEIC again in August 2024, highlighting the continuing global health threat posed by the disease [2]. As of May 2025, a total of 142,151 confirmed Mpox cases and 328 deaths had been reported across 133 countries globally, corresponding to a case fatality rate (CFR) of 0.23% [3]. By June 2025, the MPXV clade Ib was responsible for community transmission of Mpox in several African countries [4]. Human-to-human transmission was reported in countries including Burundi, the Democratic Republic of the Congo, Ethiopia, Kenya, Malawi, Rwanda, South Sudan, Tanzania, Uganda, and Zambia. The Democratic Republic of the Congo (DRC) reported the highest number of confirmed Mpox cases in Africa in 2025 [4]. Since its initial identification in the Democratic Republic of the Congo (DRC), MPXV has spread to neighboring non-endemic African countries. These include the Central African Republic (CAR) and the Republic of the Congo, where studies have reported ongoing community transmission [5,6]. To prevent avoidable deaths in both hospital and community settings, the response of health authorities in the Central African Republic (CAR) to this public health threat should be grounded in robust surveillance and healthcare systems capable of early identification, accurate diagnosis, and prompt management of all notified cases [7]. This represents a major concern, as under-resourced health systems, such as those in the Central African Republic (CAR), may be rapidly overwhelmed by the burden and severity of Mpox outbreaks. In addition, marginalized and hard-to-reach populations, including refugees, internally displaced persons, nomadic communities, and migrants, may have limited access to healthcare services, thereby increasing their vulnerability to the disease [8]. The situation in the Central African Republic (CAR) is particularly sensitive in the context of this outbreak, given its socioeconomic and political conditions. The country is among the least developed globally, and its socioeconomic status has been severely affected by decades of political instability, armed conflict, and large-scale population displacement [9]. This has resulted in high levels of poverty and food insecurity, with a significant proportion of the population living under precarious conditions and having limited access to basic necessities such as clean water and sanitation facilities. In many communities, reliance on traditional healers and informal healthcare providers may delay timely diagnosis and appropriate management of infectious diseases such as Mpox, thereby potentially exacerbating transmission and hindering effective public health responses [10,11]. In this context, prevention remains a key strategy for controlling the spread of the disease within endemic hotspots and across the country. Implementing immunization programs for populations at the highest risk of Mpox infection may strengthen the public health response to the outbreak [12,13]. These high-risk groups include individuals living in close proximity to wildlife reservoirs, particularly in forested, rural, and remote areas, where there is often a severe shortage of qualified healthcare personnel, medical supplies, and diagnostic capacity [5]. Most previous evidence on Mpox in the Central African Republic (CAR) has been based on small sample sizes, thereby limiting the generalizability of findings at the national level [5, 14-16]. A clear understanding of the disease’s evolution and regional distribution in this context is essential for designing and implementing effective Mpox prevention and control strategies tailored to the specific realities of CAR. Therefore, this study aimed to provide insights into the epidemiological and clinical profiles of multiple Mpox outbreaks reported in CAR.
2.1. Study Design The study protocol was not prospectively registered. However, the review was conducted in accordance with PRISMA guidelines [17]. 2.2. Operational Definitions In the primary studies included, a suspected Mpox case was defined as an individual presenting with a vesicular or pustular rash characterized by deep-seated, firm pustules, along with at least one of the following symptoms: fever preceding the rash, lymphadenopathy (inguinal, axillary, or cervical), or the presence of pustules or crusts on the palms of the hands or soles of the feet. A case was defined as laboratory-confirmed Mpox if at least one specimen yielded a positive result in an Orthopoxvirus-specific assay, Mpox-specific real-time polymerase chain reaction (RT-PCR), or viral culture [18,19]. Cases were classified as severe or critical (requiring hospitalization) if one or more of the following were present: extensive lesions (>100), hemorrhagic or pustular lesions, mucosal involvement (oral, genital, or conjunctival), or systemic complications. Systemic complications included high fever (>39 °C), altered general condition, sepsis, encephalitis, secondary bacterial infections, hypotension, septic shock, severe dehydration, and keratitis, which may lead to corneal scarring and blindness [4, 18, 20]. Vaccination uptake was defined as the proportion of individuals who reported having received an Mpox vaccine or who presented documented evidence of vaccination, such as an Mpox vaccination card [12,21]. 2.3. Literature Search Strategy Literature searches were conducted in PubMed, Scopus, ScienceDirect, Web of Science, Embase, the Cochrane Library, and AJOL to identify relevant studies. The screening process involved an initial review of the titles and abstracts of each retrieved study. A combination of keywords and Medical Subject Headings (MeSH) terms, along with Boolean operators, was used to refine the search strategy across all databases (Supplementary File S1, Supplementary Table S1). To ensure completeness, additional manual searches were conducted to identify relevant publications not captured in electronic databases, including Google Scholar, where the first 1,000 entries were screened without applying filters. Furthermore, the reference lists of included studies were reviewed to identify additional eligible articles. The final literature search was completed in February 2025. 2.4. Eligibility Criteria Inclusion criteria: This systematic review and meta-analysis included all eligible reports, including preprints, regardless of study design, that documented Mpox in the Central African Republic (CAR). Only articles published in English or French were considered, and no restrictions were applied to the publication date. Exclusion criteria: Studies whose research focus deviated from the objectives of the present review or duplicated findings from existing reports were excluded. In addition, letters to the editor, commentaries, and reports that did not specify sample size were not included. 2.5. Data Extraction A structured Microsoft Excel 2016 spreadsheet was used to extract and compile data from all included studies. The data extraction checklist included the first author’s name, year of publication, study region, study design, setting, number of suspected, confirmed, severe, and fatal cases, number of individuals who received the Mpox vaccine, sample size, and number of reported clinical manifestations. Two authors independently assessed each article for quality and relevance. Discrepancies between the reviewers were resolved through discussion, with input from a third reviewer to achieve consensus. 2.6. Data Quality Assessment The quality of the included studies was assessed using the Joanna Briggs Institute (JBI) critical appraisal tool for cross-sectional studies, particularly those generated from outbreak surveillance and investigation activities [22]. For cross-sectional studies, the assessment criteria included a clear definition of inclusion criteria, comprehensive description of study participants and settings, validity and reliability of exposure measurements, use of objective and standardized outcome assessment criteria, identification of potential confounding factors, implementation of appropriate strategies to address them, and the appropriateness of statistical methods used. A binary score of 0 [no or unclear] or 1 [yes] was assigned after evaluating each criterion. The overall risk of bias was categorized as low (>50%), moderate (>25–50%), or high (≤25%). 2.7. Outcome Measurement The primary outcomes of this systematic review and meta-analysis were Mpox severity and case fatality rate (CFR). The secondary outcomes included vaccination uptake and the clinical manifestations among suspected and confirmed cases. The Mpox severity rate was determined by calculating the proportion of confirmed cases with severe or critical Mpox. The case fatality rate (CFR) was calculated by dividing the number of deaths by the total number of suspected or confirmed cases. The Mpox vaccination uptake rate (coverage) was obtained by dividing the number of individuals who received the vaccine by the number of eligible participants. The frequency of each clinical manifestation was calculated by dividing the number of reported events (symptoms or signs) by the total number of suspected or confirmed cases. 2.8. Statistical Analysis and Synthesis The I2 statistic was used to assess heterogeneity of pooled estimates between studies. It was categorized as low (<25%), moderate (25−75%), or high (>75%). Subgroup analyses were performed to examine temporal trends (study period), geographical differences (study location), and disease burden. The disease burden cutoff was defined based on the median number of suspected or confirmed cases reported across the included studies. Given the evolving case definitions and diagnostic approaches, as well as conflict-related disruptions and clinical and epidemiological heterogeneity, a random-effects model was preferred over a fixed-effects model for the analysis of primary outcomes. Timeframes for this analysis were defined in relation to the global outbreak that prompted an enhanced international response [23]. Generalized linear mixed models (GLMM), combined with the logit transformation (PLOGIT), were applied to stabilize variance in pooled binomial proportions [24]. This approach is well suited for meta-analyses of binary or proportion data, as it directly models binomial outcomes and accommodates studies reporting 0% or 100% events without the need for continuity corrections. All analyses were performed using the “meta” package in R version 4.5.2 [25]. 2.9. Publication Bias and Sensitivity Analysis A funnel plot was used to visually assess publication bias. The absence of publication bias was inferred from the observed symmetry of the inverted funnel shape. To further evaluate potential bias, Egger’s regression test and Begg’s rank correlation test were performed. Sensitivity analysis was conducted by sequentially excluding one study at a time to assess the robustness of the pooled estimates.
3.1. Study Selection The initial search yielded 604 records (595 from online databases and 9 from other sources). After removing 26 duplicates, 578 records were screened based on title, abstract, and full-text assessment. Ultimately, seven studies met the inclusion criteria and were included in the analysis [5, 14-16, 26-28] (Figure 1). 3.2. Characteristics of Included Reports A total of seven studies were included in the final analysis. These studies reported findings spanning from 2010 to 2022 and involved populations from both community and hospital settings. The included studies were conducted at the national level or across different regions of the Central African Republic, including Regions 2, 4, and 6. All studies employed surveillance and outbreak investigation methodologies for data collection and used non-probability sampling techniques (Table 1). Characteristics of included studies. 1 Date of study completion; NR: Not reported; PCR: Polymerase Chain Reaction. 3.3. Disease Severity Among Confirmed Mpox Cases The overall pooled Mpox severity rate among confirmed cases was 60.92% (95% confidence interval (CI): 47.54–72.83; I2 = 9.7% and p = 0.351) (Figure 2). Subgroup analysis by study period revealed a non-significant decrease in Mpox severity rate from 66.00% (95% CI: 51.95–77.70; n = 4 reports) before 2022 [14-16, 26] to 42.86% (95% CI: 17.66–71.14; n = 1 report) after 2022 [5]. The highest severity rate was observed in region 6 (77.27%; 95% CI: 55.64–90.21; n = 2 reports) [14,26]; however, no statistically significant differences were found in severity rates across regions (p = 0.245) (Table 2 and Supplementary File S2, Supplementary Figures S1–S3). Subgroup meta-analysis of confirmed Mpox severity rate pooled estimates in CAR. 1 Random effects model; CI: Confidence interval; 2 Period before and after the 2022 global outbreak; HCW: Healthcare worker. 3.4. Mortality Among Confirmed Mpox Cases The pooled CFR among confirmed Mpox cases was 10.71% (95% CI: 4.52–23.28; I2 = 0.0% and p = 0.894) (Figure 3). All included studies were conducted prior to the global outbreak. Geographical trend analysis indicated that the highest mortality was recorded in the Eastern Health Regions (10.81%; 95% CI: 4.03–25.93) [14, 16, 26, 28], whereas the Western Health Regions reported no deaths (0.00%; 95% CI: 0.00–100.00) [28]. However, these findings should be interpreted with caution due to the small sample size of studies conducted in the Western Health Regions (n = 8 participants) (Table 3 and Supplementary File S3, Supplementary Figures S1–S3). Subgroup meta-analysis of confirmed Mpox case fatality rate pooled estimates in CAR. 1 Random effects model; CI: Confidence Interval; Western = Health Regions 1 and 2; Eastern = Health Regions 4 and 6; HCW: Healthcare worker. 3.5. Case Fatality Rate Among Suspected Mpox Cases The pooled CFR among suspected Mpox cases was 12.13% (95% CI: 5.59–24.34; I2 = 0.0% and p = 0.897) (Figure 4). The subgroup analysis showed a modest decline in the case fatality rate (CFR) among suspected Mpox cases from the pre-2022 period (12.19%; 95% CI: 4.65–28.34) [14-16, 26, 28] to the post-2022 period (9.09%; 95% CI: 0.23–41.28) [5]. Geographical disparities were observed, with higher case fatality rates (CFRs) in the Eastern Health Regions (9.95%; 95% CI: 3.39–22.71) than in the Western Health Regions (5.26%; 95% CI: 0.74–29.39). The general population CFR (10.00%, 95% CI: 3.56–29.30) [5, 15-16, 26, 28] aligns with overall trends, with no significant heterogeneity detected (I2 = 0.0–1.6%) across subgroups (Table 4 and Supplementary File S4, Supplementary Figures S1–S4). Subgroup meta-analysis of suspected Mpox case fatality rate pooled estimates in CAR. 1 Random effects model; CI: Confidence interval; 2 Period before and after the 2022 global outbreak; Western = Health Regions 1 and 2; Eastern = Health Regions 4 and 6; HCW: Healthcare worker. 3.6. Mpox Vaccine Uptake The pooled vaccination uptake estimate in the Central African Republic (CAR) was 20.00% (95% CI: 10.33–35.17), indicating that approximately eight out of ten individuals had not received active immunization against Mpox (Figure 5). 3.7. Clinical Patterns of Mpox The most frequently reported clinical manifestations among confirmed Mpox cases were fever and rash, with pooled prevalence estimates of 91.05% and 85.53%, respectively. Other commonly reported symptoms included chills or sweating (90.00%) and photophobia (88.89%); however, each was reported in only one study [5, 14-16, 26-27] (Table 5 and Figure 6). Clinical manifestations of confirmed Mpox cases in CAR. k = Number of studies; CI: Confidence interval. 3.8. Publication Bias and Sensitivity Analysis Publication bias could not be reliably assessed for the severity rate, mortality rate among confirmed cases, and vaccination uptake rate due to the limited number of included studies. However, Egger’s linear regression test and Begg’s rank correlation test indicated no statistically significant publication bias for the case fatality rate (CFR) among suspected cases (Supplementary File S2, Supplementary Figure S4; Supplementary File S3, Supplementary Figure S4; Supplementary File S4, Supplementary Figure S5; and Supplementary File S5, Supplementary Figure S1). Sensitivity analysis was performed to evaluate the influence of individual studies and potential outliers on the overall results. The analysis demonstrated that no single study had a significant effect on the pooled estimates (Supplementary Files S2, S3, S4; Supplementary Figure S5).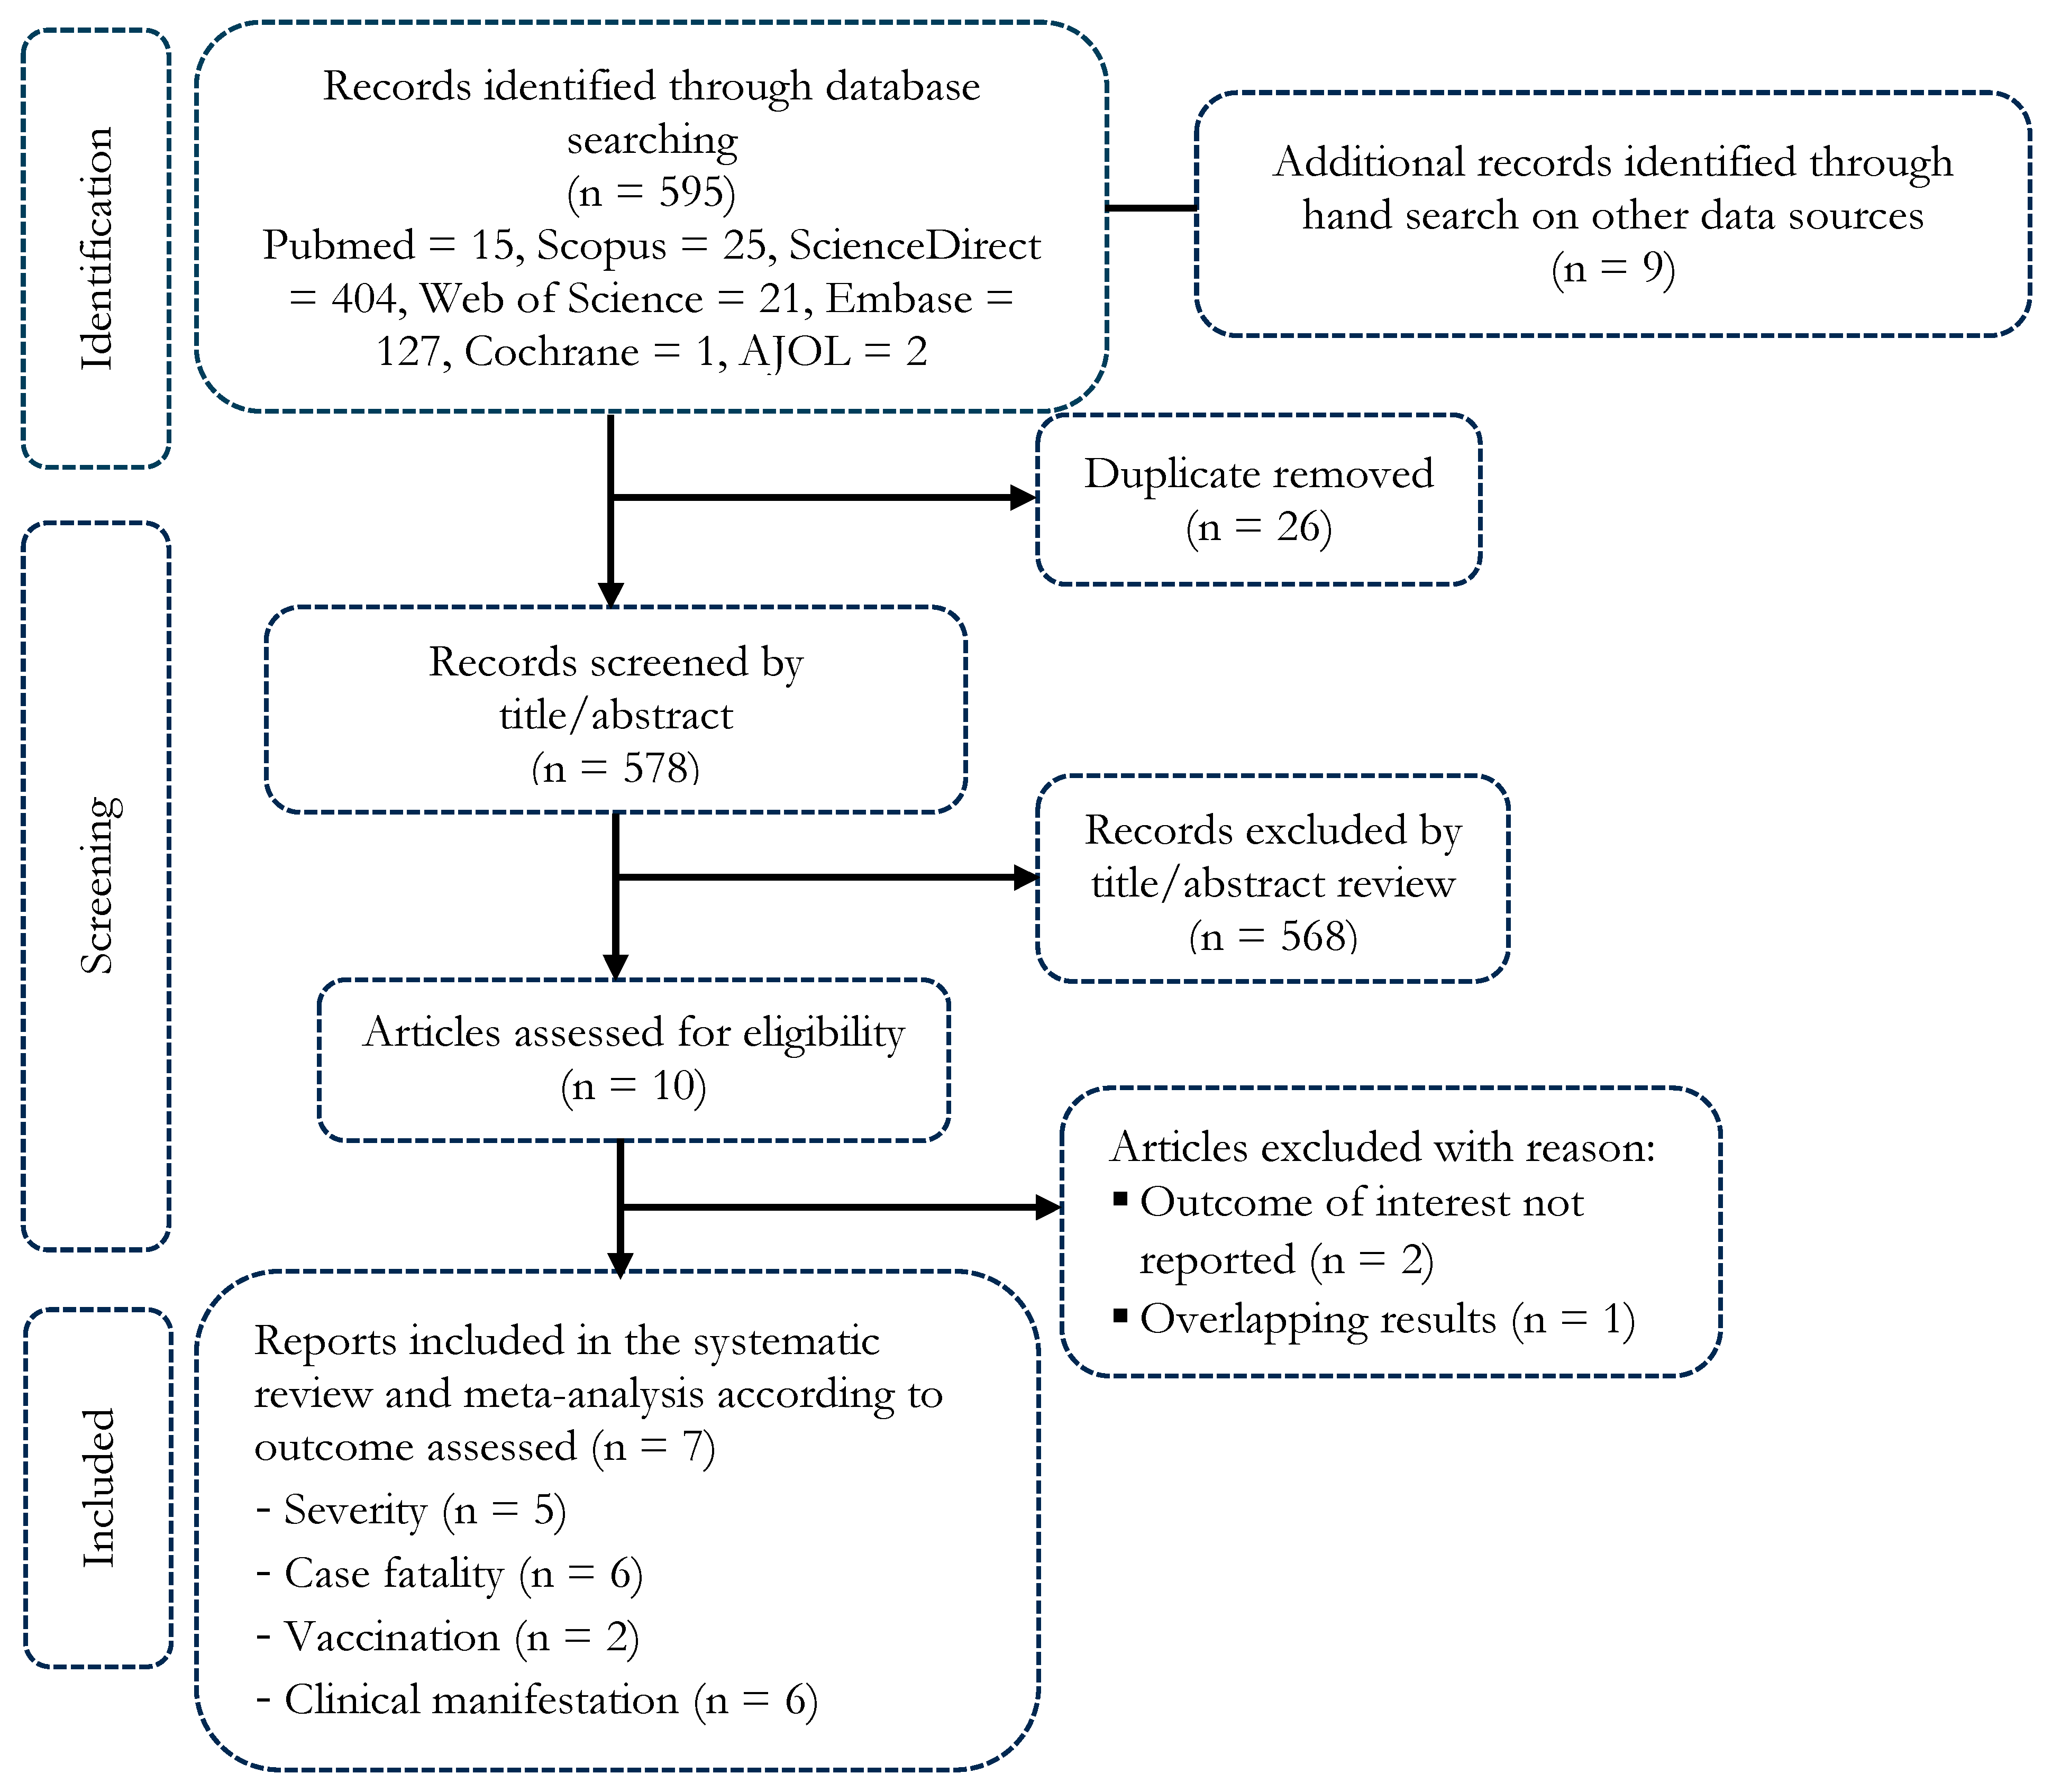 Table 1:
Author
Study
Year 1Region
Setting
Study Population
Sampling
Risk of Bias
Outcome of Interest
Summary of Findings
Durski et al. [28]
2017
Multicentric
Community
General population
Non-probabilistic
Moderate
Case fatality rate
Since 2016, cases have been confirmed in the Central African Republic (19 cases), the Democratic Republic of the Congo (>1000 reported per year), Liberia (two), Nigeria (>80), the Republic of the Congo (88), and Sierra Leone (one). The reemergence of monkeypox is a global health security concern.
Berthet et al. [15]
2010
NR
Community
General population
Non-probabilistic
Low
Severity and case fatality rates
In June 2010, two teenage boys in the Central African Republic developed pustular skin lesions after eating a wild rodent, later confirmed as monkeypox virus (identical to the DRC strain from a 2001 outbreak). Both recovered after isolation and treatment, highlighting monkeypox’s zoonotic risk in forested regions.
Kalthan et al. [26]
2016
Region 4
Community
General population
Non-probabilistic
Low
Severity, case fatality, and vaccine uptake rates
A study identified 26 monkeypox cases, with the highest attack rates in children (<10 years) and young adults (21–30 years). The overall attack rate was 5 per 1000 inhabitants; severe disease occurred predominantly (87.5% of cases) in unvaccinated younger individuals.
Kalthan et al. [16]
2015
Region 6
Community
General population
Non-probabilistic
Low
Severity and case fatality rates
A 2015–2016 monkeypox outbreak in Bangassou, Central African Republic, affected 12 patients (mostly adults aged 31–40 and children under 10), with a 25% fatality rate (67% in children). The disease, characterized by fever, rash, and lymphadenopathy (54.5%), had an attack rate of 0.2/1000 inhabitants, underscoring the need for isolation, community education, and surveillance of animal reservoirs to curb transmission.
Nakoune et al. [14]
2016
Region 6
Community
General population and healthcare workers
Non-probabilistic
Moderate
Severity and case fatality rates
A 2015/2016 familial monkeypox outbreak in the Central African Republic infected 10 individuals through household, healthcare, and transport-related transmission. The Zaire genotype strain caused characteristic fever and skin lesions, with two fatal pediatric cases highlighting the disease’s severity in children.
Besombes et al. [27]
2018
Region 1
Community
General population and healthcare workers
Non-probabilistic
Moderate
Severity, case fatality, and vaccine uptake rates
In September 2018, a monkeypox outbreak involving an Aka Pygmy family in the Central African Republic began when a 25-year-old woman developed symptoms after butchering wild animals, leading to three waves of intrafamilial transmission that ultimately infected five family members. While PCR confirmed six cases (including three children), serologic evidence suggested that prior Orthopoxvirus exposure may have limited secondary spread, highlighting the role of zoonotic exposure and the waning protection conferred by historic smallpox vaccination campaigns.
Besombes et al. [5]
2022
Region 2
Community
General population
Non-probabilistic
Low
Severity and case fatality rates
A November 2021 monkeypox outbreak in the Central African Republic originated from a hunter’s contact with a primate, sparking four transmission waves across two families with a 59.5% secondary attack rate (14 confirmed cases). The clade I virus caused severe complications (63.2% of cases), including bronchopneumonia and skin sequelae, with 4% mortality, demonstrating both the high transmissibility and clinical severity of endemic strains that risk international spread
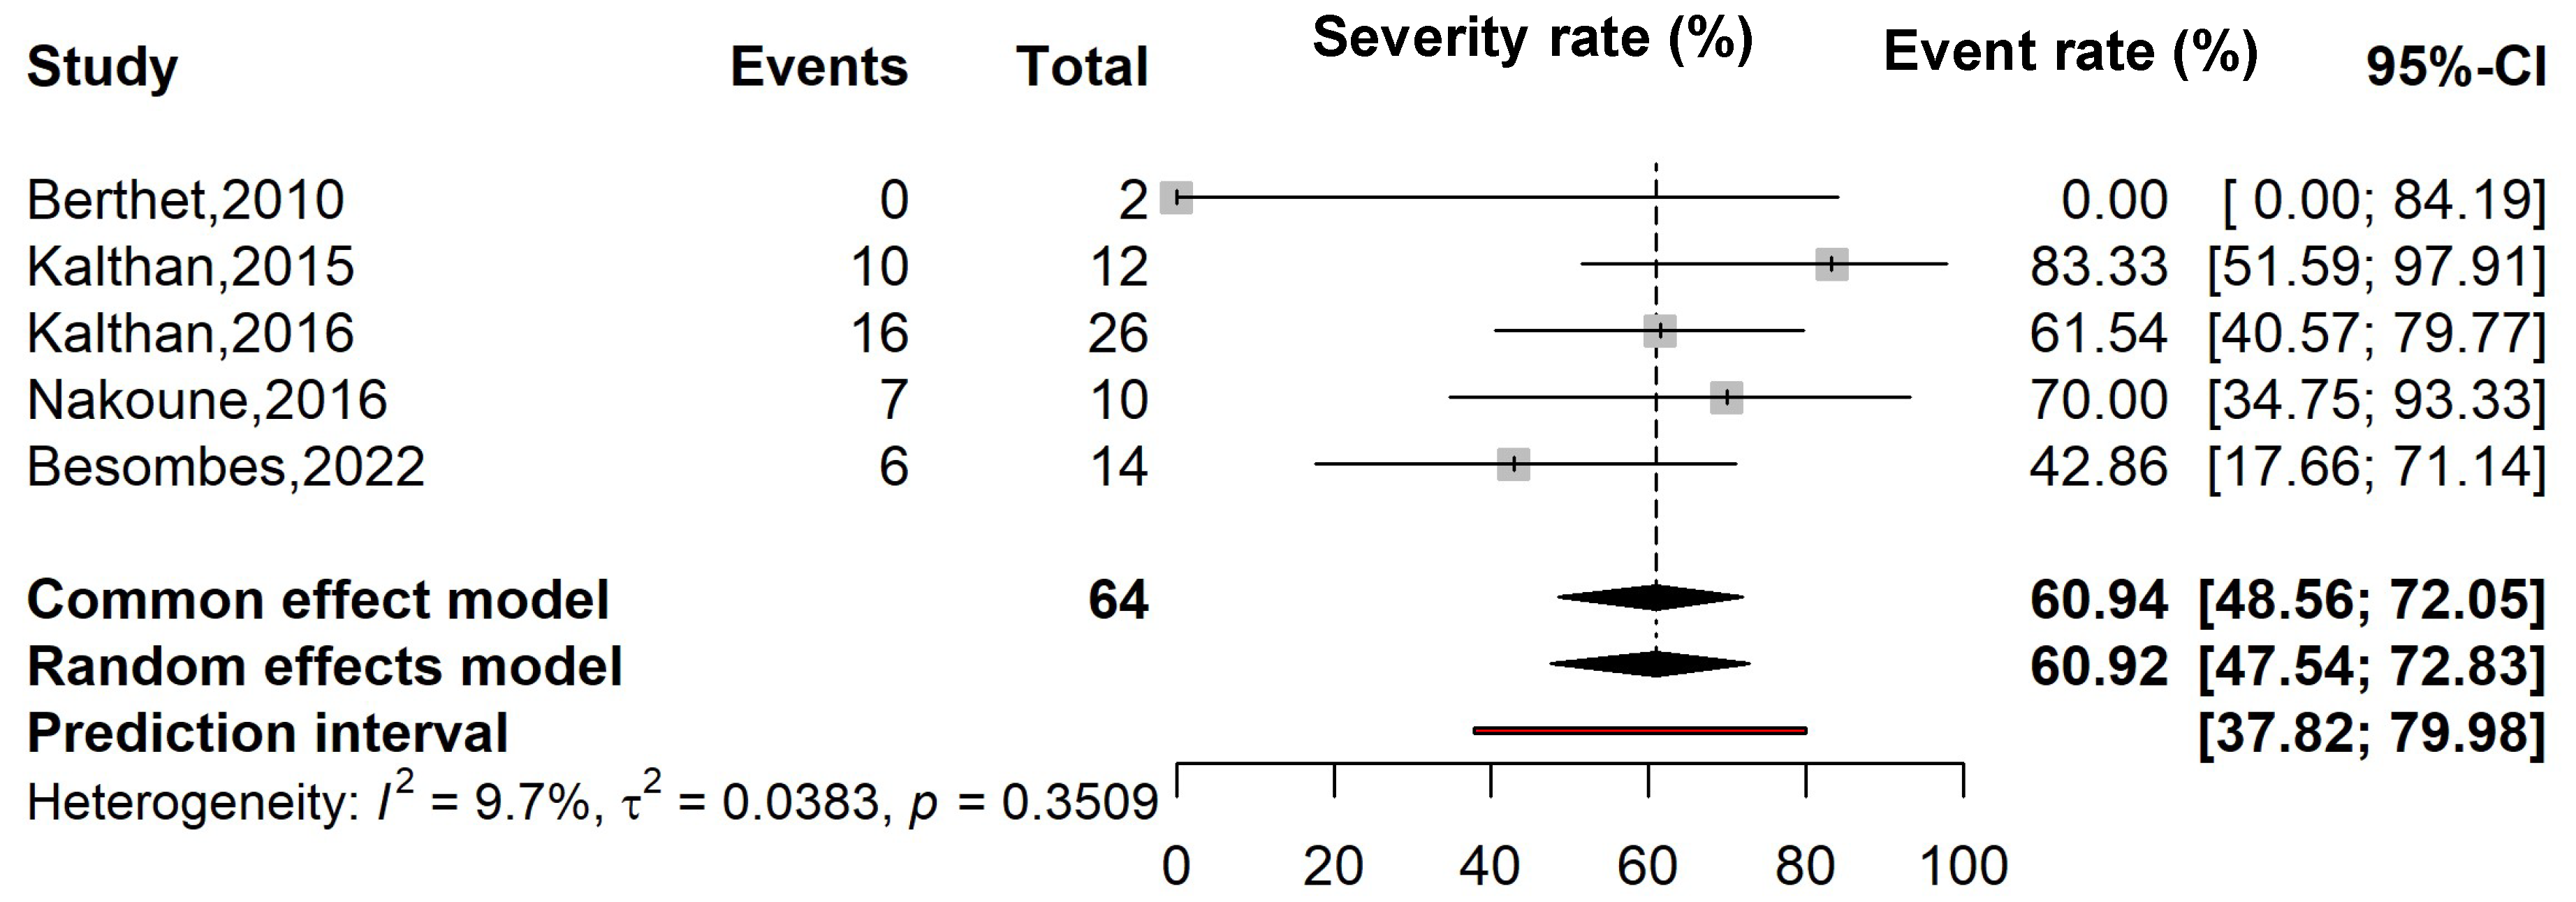 Table 2:
Subgroup
Confirmed Cases
Event Rate 1 (%)
95% CI Limits 1
Number of Studies
Heterogeneity Statistic 1
Lower
Upper
I2(%)
p-Value
Period 2
˂2022
50
66.00
51.95
77.70
4
0
0.630
2022+
14
42.86
17.66
71.14
1
-
-
Region
Region 2
14
42.86
17.66
71.14
1
-
-
Region 4
26
61.54
40.57
79.77
1
-
-
Region 6
22
77.27
55.64
90.21
2
0
0.463
Not specified
2
0.00
0.00
84.19
1
-
-
Participant
General population
54
58.52
40.09
74.84
4
26.6
0.252
General population and HCW
10
70
34.75
93.33
1
-
-
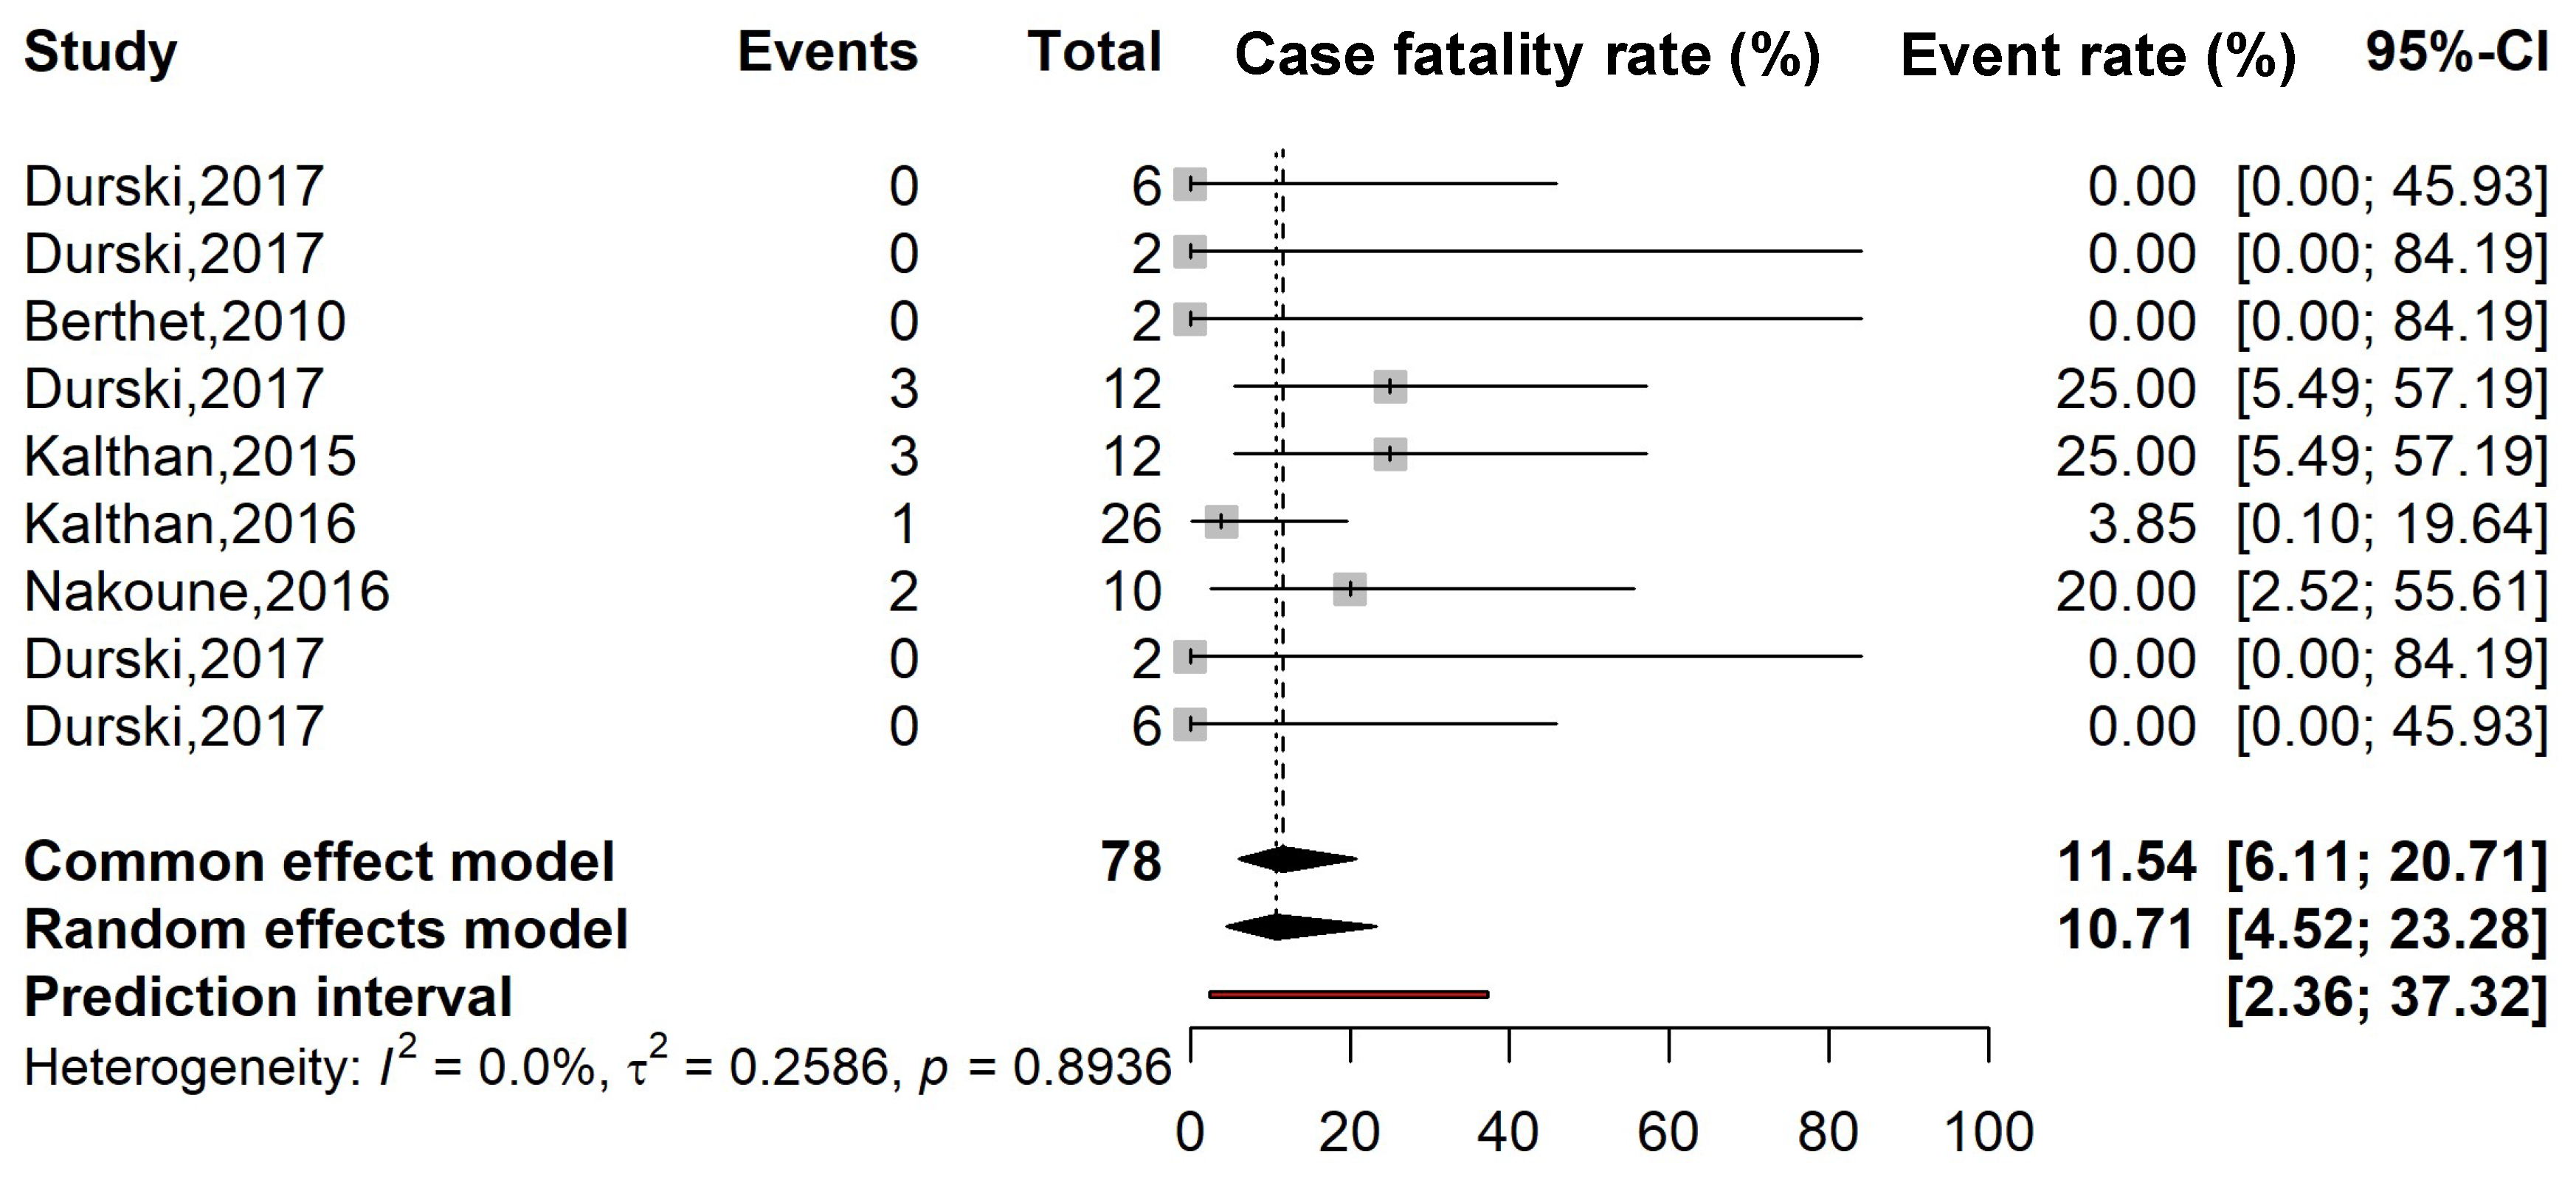 Table 3:
Subgroup
Confirmed Cases
Event Rate 1 (%)
95% CI Limits 1
Number of Studies
Heterogeneity Statistic 1
Lower
Upper
I2(%)
p-Value
Region
Region 1
2
0.00
0.00
84.19
1
-
-
Region 2
6
0.00
0.00
45.93
1
-
-
Region 4
26
3.85
0.10
19.64
1
-
-
Region 6
28
17.86
7.63
36.38
3
0.0
0.962
Multicentric
12
25.00
5.49
57.19
1
-
-
Not specified
4
0.00
0.00
100.00
2
0.0
1.000
Region group
Western
8
0.00
0.00
100.00
2
0.0
1.000
Eastern
54
10.81
4.03
25.93
4
5
0.368
Multicentric
12
25.00
5.49
57.19
1
-
-
Not specified
4
0.00
0.00
100.00
2
-
-
Participant
General population
68
8.56
2.51
25.34
8
0.0
0.894
General population and HCW
10
20.00
2.52
55.61
1
-
-
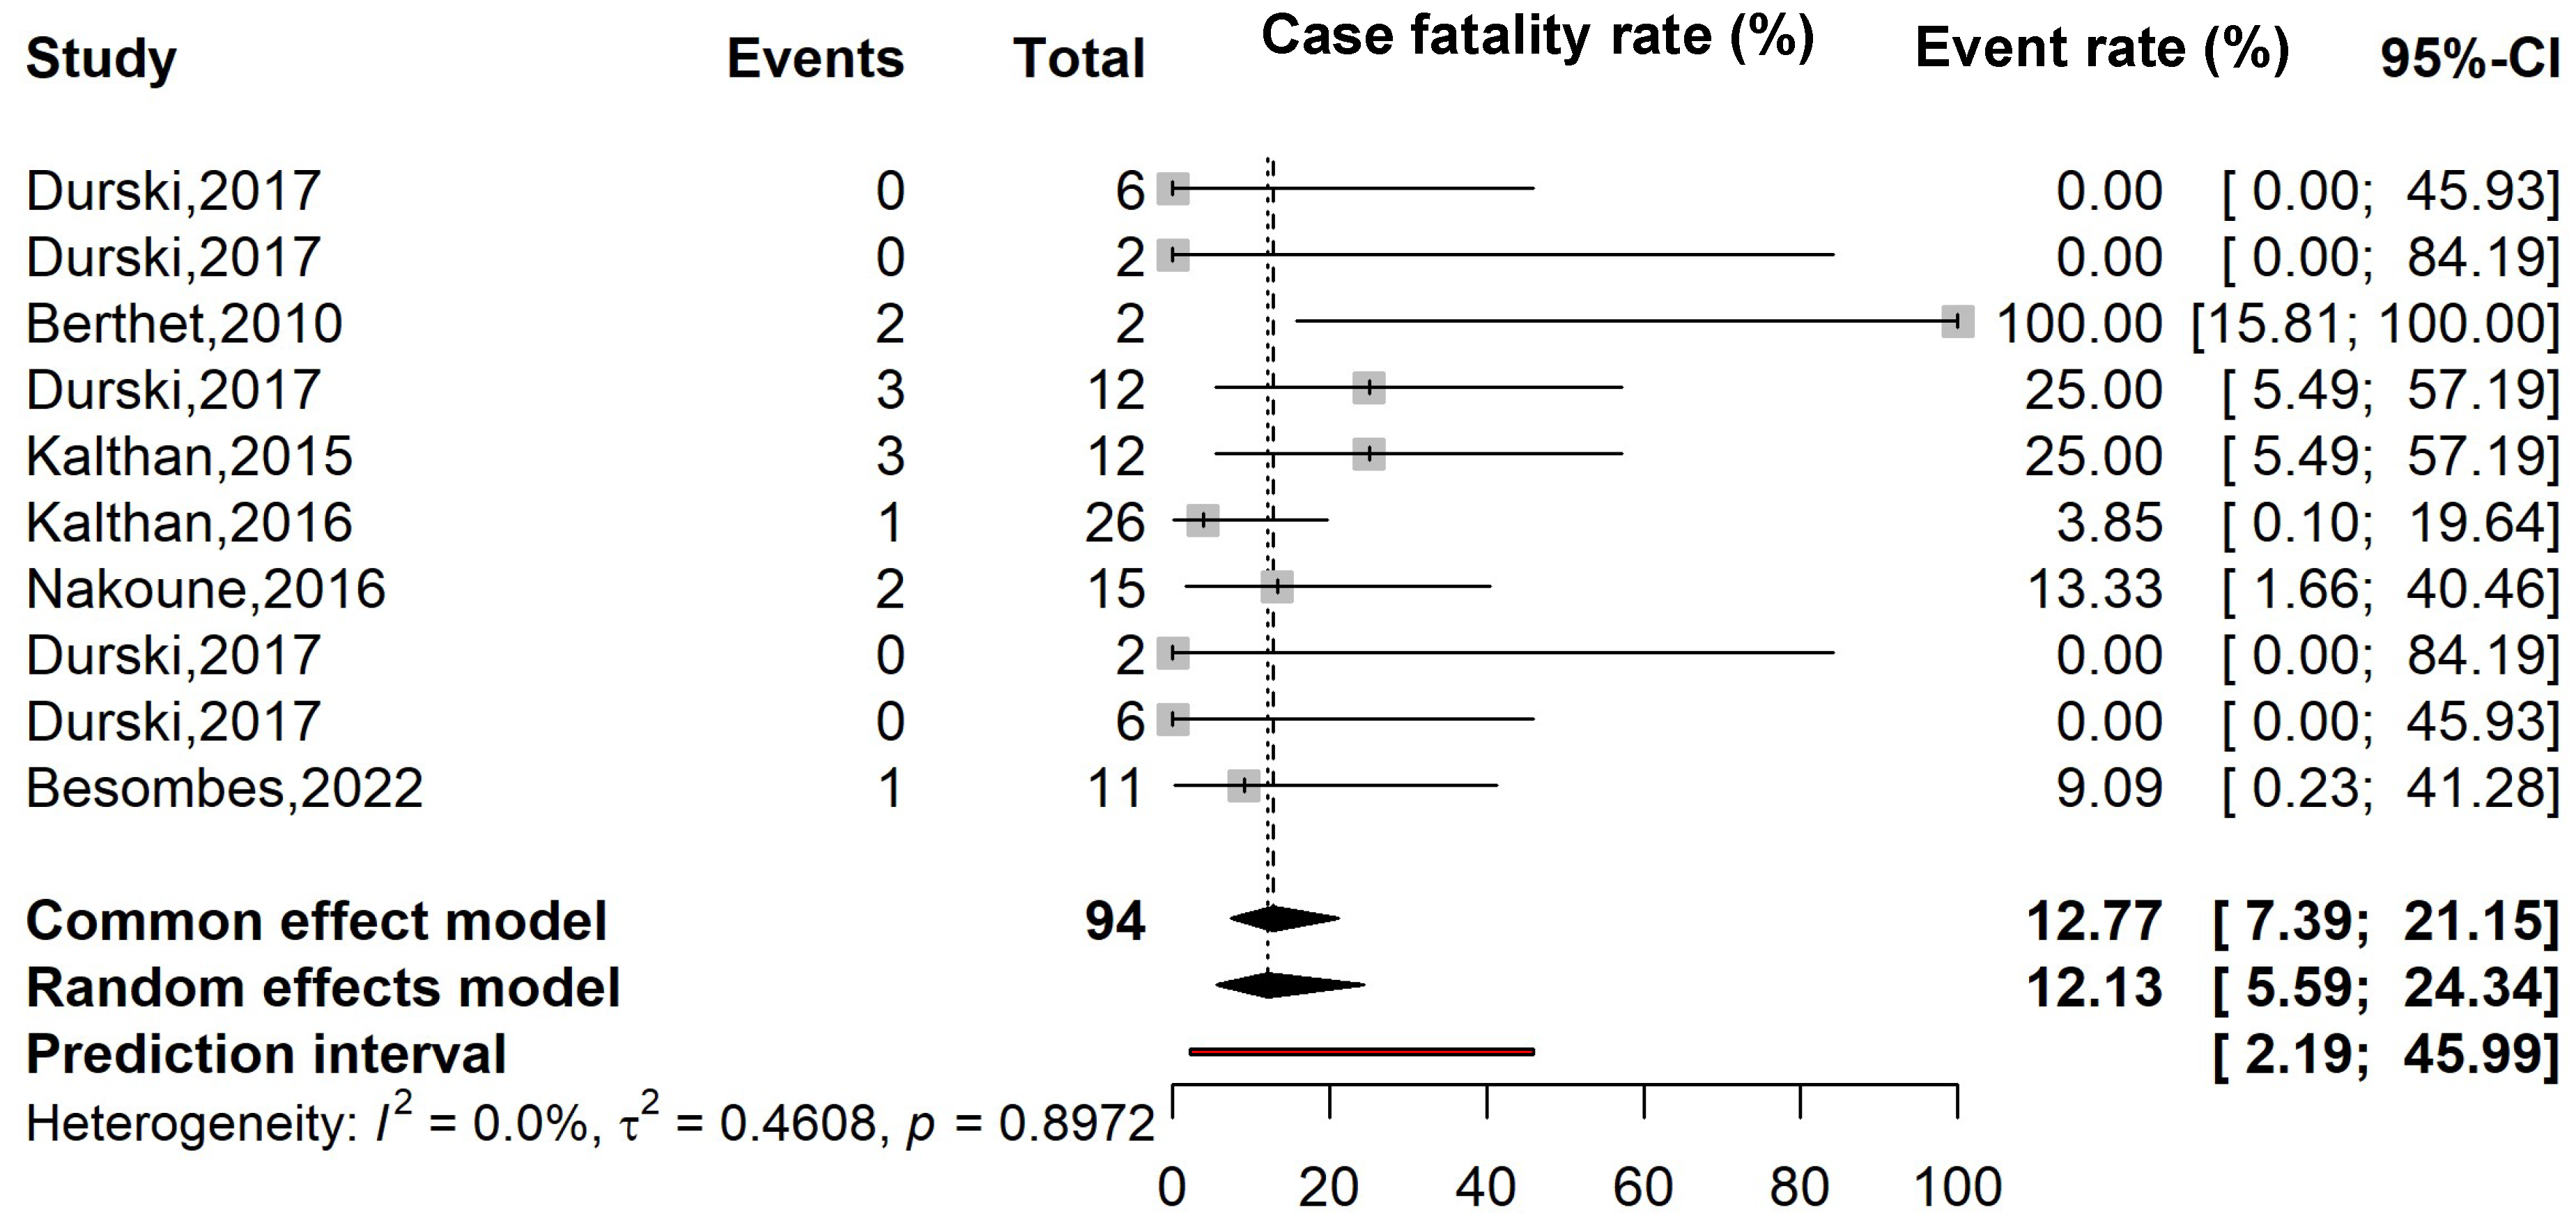 Table 4:
Subgroup
Suspected Cases
Event Rate 1 (%)
95% CI Limits 1
Number of Studies
Heterogeneity Statistic 1
Lower
Upper
I2(%)
p-Value
Period 2
˂2022
83
12.19
4.65
28.34
9
0.0
0.877
2022+
11
9.09
0.23
41.28
1
-
-
Region
Region 1
2
0.0
0.18
33.87
1
-
-
Region 2
17
5.88
0.82
32.03
2
0.0
0.999
Region 4
26
3.85
0.10
19.64
1
-
-
Region 6
33
15.15
6.45
31.62
3
0.0
0.746
Multicentric
12
25.00
5.49
57.19
1
-
-
National
14
7.14
0.18
33.87
1
-
-
Not specified
4
0.00
0.00
99.99
2
0.0
0.999
Region group
Western
19
5.26
0.74
29.39
3
0.0
1.000
Eastern
59
9.95
3.99
22.71
4
1.6
0.384
Multicentric/National
12
25.00
5.49
57.19
1
-
-
Not specified
4
0.00
0.00
99.99
2
0.0
0.999
Participant
General population
125
11.00
3.56
29.30
14
0.0
0.848
General population and HCW
15
13.33
1.66
40.46
1
-
-
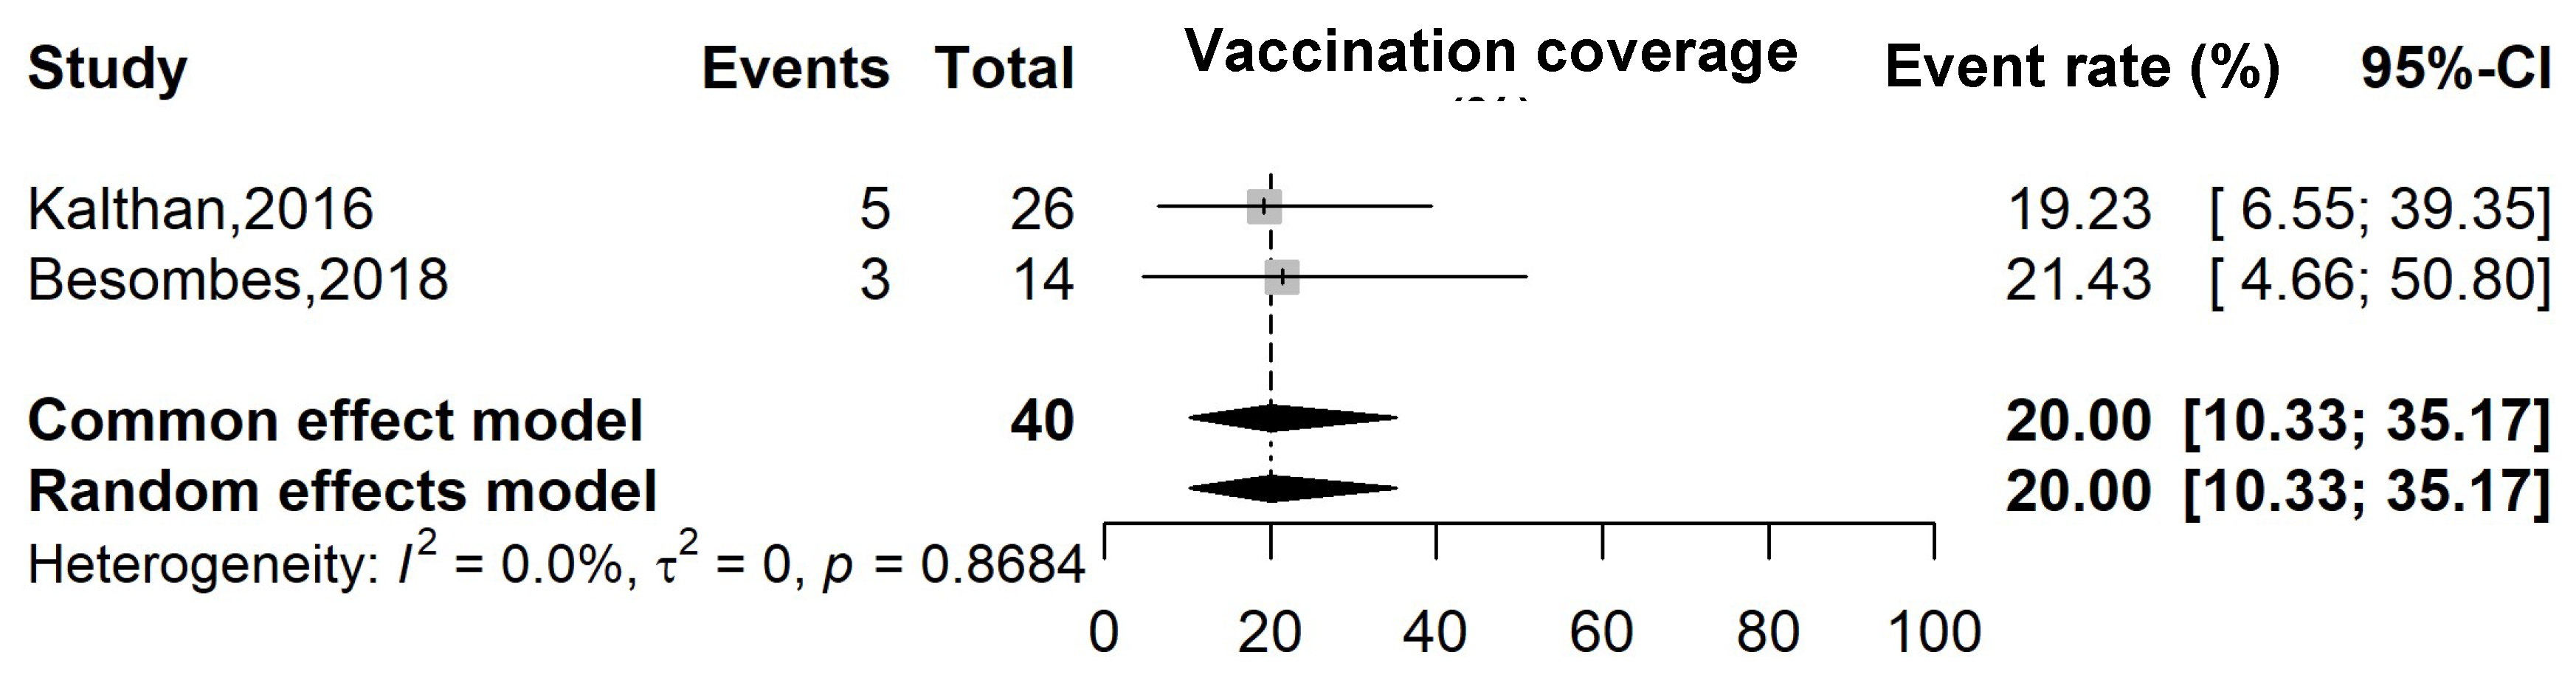
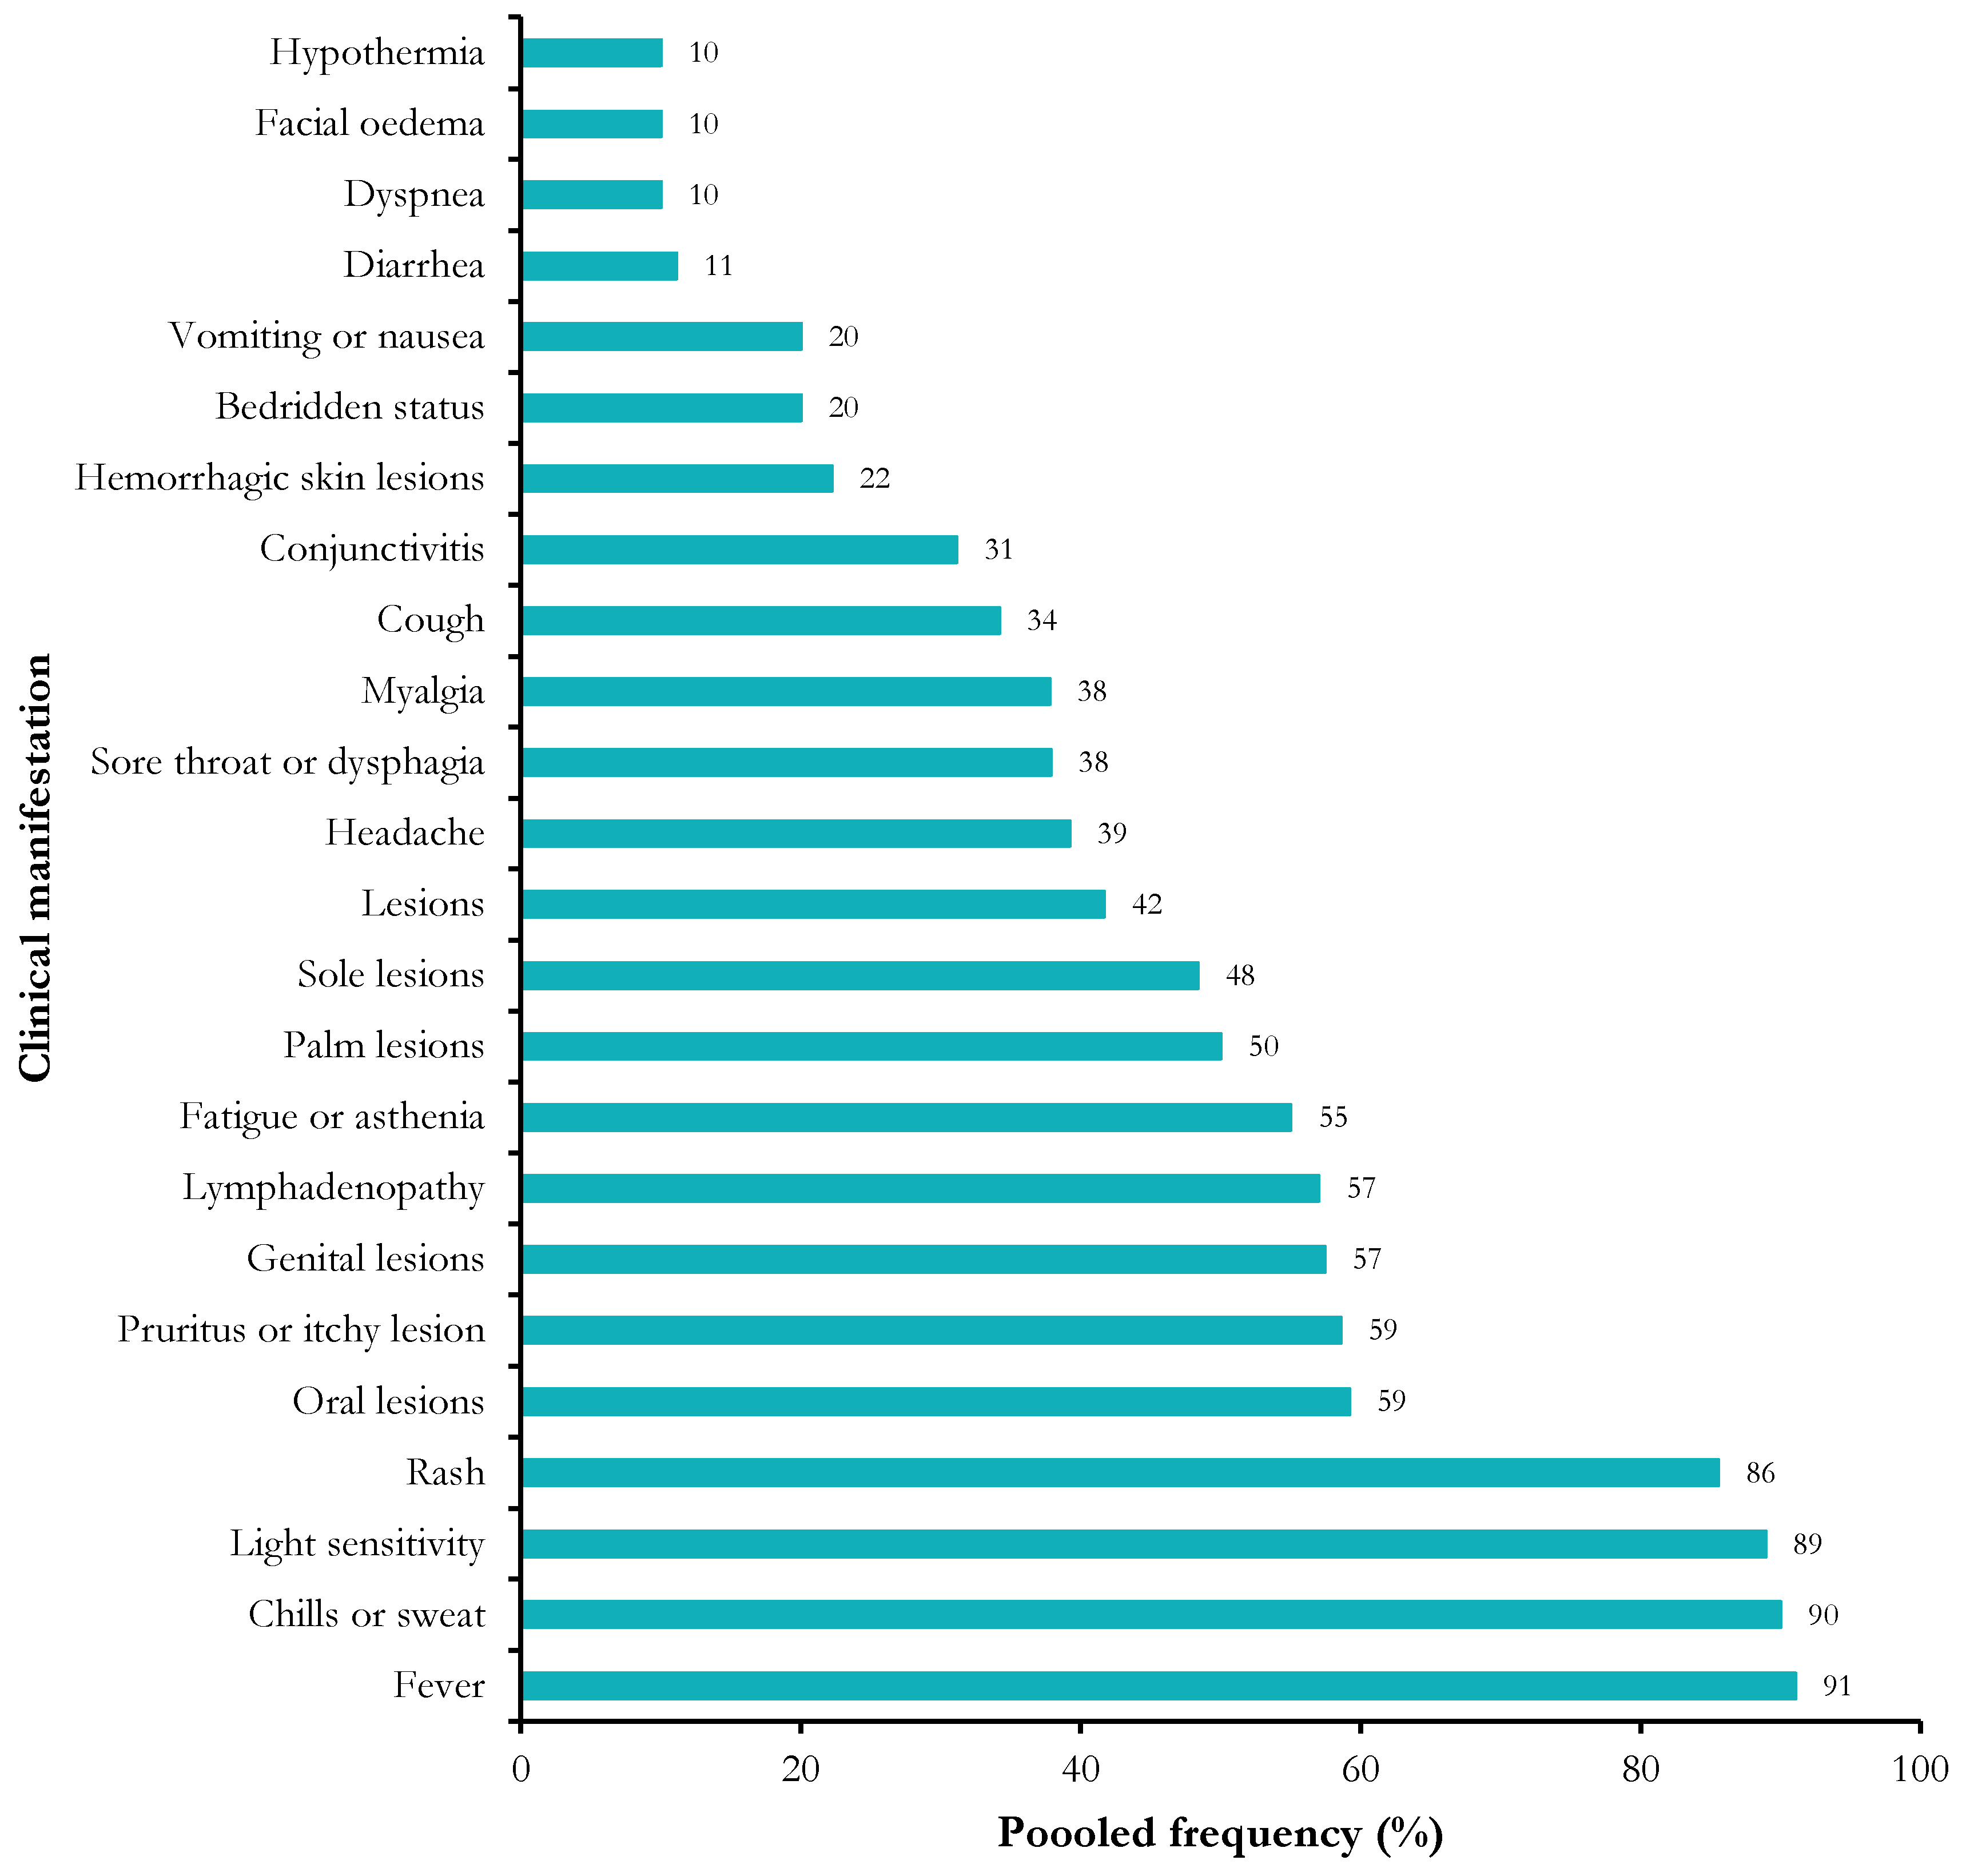 Table 5:
Rank
Clinical Manifestation
Confirmed Cases Examined (n)
Frequency (%)
95% CI Limits
k
Heterogeneity Statistic
Model
Lower
Upper
I
2 (%)
p
-Value
1
Fever
70
91.05
42.88
99.28
5
74.1
0.004
Random
2
Chills or sweat
10
90.00
55.50
99.75
1
-
-
-
3
Light sensitivity
9
88.89
51.75
99.72
1
-
-
-
4
Rash
76
85.53
75.72
91.80
6
15.8
0.312
Fixed
5
Oral lesions
20
59.16
8.56
95.73
2
86.5
0.007
Random
6
Pruritus or itchy lesion
46
58.57
31.53
81.27
3
59.1
0.087
Random
7
Genital lesions
19
57.43
8.76
94.99
2
85.4
0.009
Random
8
Lymphadenopathy
58
57.00
34.27
77.12
4
57.2
0.072
Random
9
Fatigue or asthenia
20
55.00
33.62
74.68
2
0.0
0.999
Fixed
10
Palm lesions
20
50.00
3.03
96.97
2
88.5
0.003
Random
11
Sole lesions
19
48.36
3.12
96.46
2
87.8
0.004
Random
12
Lesions
12
41.67
15.17
72.33
1
-
-
-
13
Headache
45
39.22
7.56
83.58
3
78.5
0.010
Random
14
Sore throat or dysphagia
35
37.87
11.67
73.76
2
83.5
0.014
Random
15
Myalgia
45
37.78
24.94
52.59
3
0.0
0.5770
Fixed
16
Cough
36
34.18
5.91
81.10
2
89.7
0.002
Random
17
Conjunctivitis
20
31.14
6.38
75.00
2
77.4
0.035
Random
18
Hemorrhagic skin lesions
9
22.22
2.81
60.01
1
-
-
-
19
Bedridden status
10
20.00
2.52
55.61
1
-
-
-
20
Vomiting or nausea
10
20.00
2.52
55.61
1
-
-
-
21
Diarrhea
9
11.11
0.28
48.25
1
-
-
-
22
Dyspnea
10
10.00
0.25
44.50
1
-
-
-
23
Facial oedema
10
10.00
0.25
44.50
1
-
-
-
24
Hypothermia
10
10.00
0.25
44.50
1
-
-
-
This comprehensive systematic review and meta-analysis synthesized evidence from seven studies conducted in the Central African Republic (CAR) between 2010 and 2022. The findings provide insights into the epidemiological, clinical, and public health patterns of Mpox in CAR. The observed case fatality rate (CFR) among confirmed cases was 10.71%, which is higher than that reported in recent global outbreaks, where most studies have consistently documented CFRs below 1% [6, 23, 29]. However, these findings corroborate earlier evidence from the Democratic Republic of the Congo (DRC), where surveillance reports conducted between 2001 and 2013 revealed case fatality rates ranging from 6% to 10.6%, particularly among children and unvaccinated individuals [30,31]. Furthermore, similar mortality rates were described in the CAR during earlier outbreaks in the 1980s [32]. The high CFR in CAR could be attributed to several factors, including the endemic circulation of the more virulent Clade I Mpox virus, limited access to healthcare services, poor health-seeking behavior, and frequent delays in case detection and isolation, particularly in rural communities [33,34]. These findings highlight the need for strengthened and resilient healthcare systems to reduce mortality. The analysis showed a higher case fatality rate among confirmed Mpox cases in the Eastern Health Regions (10.81%) than in the Western Regions (0.0%). The Eastern areas include regions most affected by the prolonged conflict following the 2013 armed conflict, including Haute-Kotto, Vakaga, Mbomou, and Ouham [35]. These regions have experienced repeated armed violence, mass displacement, and targeted attacks on health facilities, which have severely compromised access to healthcare services. Médecins Sans Frontières and other humanitarian organizations have reported recurrent looting, destruction of infrastructure, and limited access to essential health services in conflict-affected health districts such as Batangafo, Bambari, and Bangassou [36]. The persistent insecurity continues to hinder timely diagnosis, isolation, and treatment of Mpox cases. These conflict-driven vulnerabilities likely contribute significantly to the elevated mortality. This underscores the urgent need for resilient healthcare systems capable of functioning effectively in contexts of political instability and violence in order to reduce Mpox-related mortality in the Central African Republic (CAR). The Central African Republic’s (CAR) extensive border with the Mpox epicenter in the Democratic Republic of the Congo (DRC) significantly increases the risk of Mpox virus (MPXV) transmission, particularly in Health Region 6, where the highest disease severity rate was recorded. The dense forest ecosystems in this border region, combined with local populations’ reliance on hunting, gathering, and agricultural activities, increase human–animal interactions and thereby facilitate zoonotic spillover [37]. The increased MPXV transmission observed in these communities, as well as the heightened risk of severe disease in this context, is likely attributable to a combination of cross-border movement and traditional livelihood practices in forested areas. Among confirmed Mpox cases in the Central African Republic (CAR), the most commonly reported clinical manifestations included fever (91%), rash (86%), photophobia (89%), and fatigue (55%). These clinical presentations are consistent with earlier descriptions of Clade I infections, which are known to cause systemic illness with associated complications. Such complications include secondary bacterial infections, dehydration, and acute respiratory distress [15,30]. The World Health Organization (WHO) has previously identified Clade I as being associated with more severe and widespread disease, as well as higher rates of complications and mortality compared with Clade II [38]. However, the Mpox outbreaks in 2022–2023, which were primarily caused by Clade IIb, had milder clinical profiles. A multinational cohort study across 16 countries reported that most patients presented with localized anogenital lesions accompanied by minimal systemic symptoms, and fewer than 10% of cases required hospitalization [23]. Similarly, another study observed that although pain was a common symptom, particularly in cases involving perianal lesions, life-threatening complications were rare, and the case fatality rate was negligible [29]. In many African countries, where timely access to quality and affordable healthcare remains limited, these differences in clinical manifestations, including the occurrence of complications, likely reflect both virological variations and disparities in healthcare infrastructure. Underreporting represents a major challenge in the Central African Republic (CAR), likely leading to an underestimation of the true burden of Mpox reported over the years. Communities living in rural or remote areas often lack access to quality healthcare, including diagnostic testing and qualified healthcare workers [39]. Studies have highlighted that several cases may go undetected for every confirmed Mpox case in endemic areas due to inadequate surveillance [40]. Moreover, Mpox symptoms can be mistaken for other endemic diseases, such as varicella, measles, or bacterial skin infections, leading to misclassification and diagnostic delays [41]. Inadequate testing capacity and suboptimal reporting rates further hinder effective epidemic response, contact tracing, and understanding of viral evolution. The review showed low vaccination uptake in the Central African Republic (CAR) (20.0%). These findings corroborate evidence from the neighboring Democratic Republic of the Congo (DRC) [31]. This may be attributed to vaccine hesitancy within the population, vaccine supply constraints, and limited healthcare infrastructure. Historically, Orthopoxvirus-derived vaccination has provided cross-protection against Mpox, with an estimated efficacy of approximately 85% [42]. However, after the worldwide smallpox vaccination program was discontinued in 1980, the number of susceptible individuals in endemic regions increased [43]. Countries with weak immunization infrastructure, such as the Central African Republic (CAR), have consequently lacked access to newer Mpox-specific vaccines as well as sustained protection derived from historical smallpox vaccination programs. Conversely, high-income countries rapidly implemented targeted vaccination campaigns during the 2022 Mpox outbreak. For example, the United States administered over 1.2 million doses of JYNNEOS, a live, non-replicating smallpox and Mpox vaccine, by early 2023, prioritizing healthcare workers and high-risk populations, including men who have sex with men [44]. Similarly, the United Kingdom implemented a pre-exposure prophylaxis campaign using a ring vaccination strategy [45]. These disparities highlight persistent global health inequities in vaccine distribution and research funding for endemic countries such as the Central African Republic (CAR), where Mpox morbidity and mortality have had long-standing public health impacts.
This systematic review and meta-analysis provide valuable insights into Mpox severity, mortality, and the clinical profile of confirmed cases, which may support the development of a context-specific Mpox case definition for the Central African Republic (CAR). The findings highlight the continued public health importance of Mpox in the region and underscore the need for sustained surveillance, further research on vaccination uptake, and targeted interventions to reduce the disease burden. However, this review has several limitations. First, some deaths may have been unreported due to study design limitations, potentially leading to an underestimation of the true case fatality rate (CFR). In addition, confounding due to viral strain differences remains a concern, as the lack of comprehensive genomic data in many studies limits the ability to assess clade-specific mortality rates. Surveillance bias, particularly improved detection of milder cases in more recent studies, may also have influenced the case fatality rate (CFR) estimates. Additionally, the small sample sizes in some subgroup analyses resulted in wide confidence intervals, thereby limiting the precision of the findings. Furthermore, studies published in languages other than English and French were not included in the search strategy.
In the Central African Republic (CAR), Mpox remains a significant public health concern due to its high case fatality and severity rates. This epidemiological profile is largely attributable to the circulation of the more virulent Clade I virus and reflects low vaccination coverage, limited access to healthcare services, and insufficient investment in surveillance systems for early disease detection. These deficiencies in Mpox case management should be further investigated and validated through future national studies. Accordingly, improved resource allocation, targeted vaccine delivery, community education, and healthcare worker training are essential to address these structural disparities in the global response to Mpox.
CAR
Central African Republic
CFR
Case Fatality Rate
CI
Confidence Interval
DRC
Democratic Republic of Congo
HCW
Healthcare Worker
MeSH
Medical Subject Headings
Mpox
Monkeypox
MPXV
Monkeypox Virus
PRISMA
Preferred Reporting Items for Systematic Reviews and Meta-Analyses
WHO
World Health Organization
Conceptualization: F.Z.L.C.; Methodology: F.Z.L.C., C.A, D.R.T. and L.B.K.B.; Data curation: F.Z.L.C.; Software: F.Z.L.C.; Validation: F.Z.L.C.; Formal analysis: F.Z.L.C.; Investigation: F.Z.L.C., C.A, and D.R.T.; Resources: All authors; Writing—original draft preparation: F.Z.L.C., C.A, and L.B.K.B.; Writing—review and editing: All authors; Visualization: F.Z.L.C. and N.G-T.; Supervision: F.Z.L.C. and N.G-T.; Project administration: F.Z.L.C. All authors have read and agreed to the published version of the manuscript.
The data sources supporting this systematic review are provided in the references. All data generated or analyzed during the study are included in this published article and its supplementary materials.
The authors declare no conflicts of interest.
The study did not receive any external funding and was conducted using only authors’ resources.
This systematic review was conducted and reported in accordance with the PRISMA (Preferred Reporting Items for Systematic Reviews and Meta-Analyses) guidelines.
Declared none.
The AI tools (Gemini and DeepSeek) were used to assist with grammatical correction and improve coherence and flow across sections of the text. The authors take full responsibility for the content and findings presented in this study.
The supplementary material associated with this article can be downloaded here.
[1] Ebede, S.O.; Orabueze, I.N.; Maduakor, U.C.; Nwafia, I.N.; Ohanu, M.E. Recurrent Mpox: Divergent Virulent Clades and the Urgent Need for Strategic Measures Including Novel Vaccine Development to Sustain Global Health Security. BMC Infect. Dis. 2025, 25, 536. [CrossRef]
[2] WHO. In First Meeting of the International Health Regulations (2005) Emergency Committee Regarding the Upsurge of Mpox 2024; WHO: Geneva, Switzerland, 2024.
[3] WHO. Multi-Country Outbreak of Mpox, External Situation Report #53—29 May 2025; WHO: Geneva, Switzerland, 2025; Available online: https://www.who.int/publications/m/item/multi-country-outbreak-of-mpox--external-situation-report--53---29-may-2025 (accessed on 1 July 2025).
[4] Cheuyem, F.Z.L.; Zemsi, A.; Ndungo, J.H.; Achangwa, C.; Takpando-le-grand, D.R.; Goupeyou-Youmsi, J.; Dabou, S.; Adama, M.; Nouko, A.; Mbang, M.A.; et al. Mpox Severity and Mortality in the Most Endemic Focus in Africa: A Systematic Review and Meta-Analysis (1970–2024). medRxiv 2025 preprint. [CrossRef]
[5] Besombes, C.; Mbrenga, F.; Malaka, C.; Gonofio, E.; Schaeffer, L.; Konamna, X.; Selekon, B.; Namsenei-Dankpea, J.; Lemon, C.G.; Landier, J.; et al. Investigation of a Mpox Outbreak in Central African Republic, 2021–2022. One Health 2023, 16, 100523. [CrossRef] [PubMed]
[6] CDC. Mpox in the United States and Around the World: Current Situation; CDC: Atlanta, GA, USA, 2025. Available online: https://www.cdc.gov/mpox/situation-summary/index.html (accessed on 1 July 2025).
[7] WHO. Africa CDC and WHO Update Mpox Strategy as Outbreaks Persist. Available online: https://www.who.int/news/item/17-04-2025-africa-cdc-and-who-update-mpox-strategy-as-outbreaks-persist (accessed on 1 July 2025).
[8] OIM. Mpox Preparedness and Response Plan for Africa 2025|Global Crisis Response Platform; OIM: Geneva, Switzerland, 2024; Available online: https://crisisresponse.iom.int/response/mpox-preparedness-and-response-plan-africa-2025 (accessed on 1 July 2025).
[9] Kostandova, N.; OKeeffe, J.; Ali, B.B.; Somsé, P.; Mahieu, A.; Bingou, O.G.; Dackpa, S.; Mbonimpa, G.; Rubenstein, L. It’s Normal to Be Afraid: Attacks on Healthcare in Ouaka, Haute-Kotto, and Vakaga Prefectures of the Central African Republic, 2016–2020. Confl. Health 2024, 18, 54. [CrossRef]
[10] Liu, E.; Sun, L. 32. Protecting the Vulnerable. Infect. Dis. Emerg. 2025, 1, 22. [CrossRef]
[11] Tosam, M.J.; Ambe, J.R.; Chi, P.C. Global Emerging Pathogens, Poverty and Vulnerability: An Ethical Analysis. In Socio-Cultural Dimensions of Emerging Infectious Diseases in Africa; Springer International Publishing: Cham, Switzerland, 2019; pp. 243–253. [CrossRef]
[12] Cheuyem, F.Z.L.; Amani, A.; Umar, A.A.; Achangwa, C.; Ajong, B.N.; Dabou, S.; Goupeyou-Youmsi, J.; Ndibo, G.R.P.; Tchamani, R.; Eno, E.A.; et al. Mpox Vaccine Uptake in the Most Endemic Focus in Africa: A Systematic Review and Meta-Analysis (1970–2024). medRxiv 2025 preprint. [CrossRef]
[13] Du, M.; Deng, J.; Yan, W.; Liu, M.; Liang, W.; Niu, B.; Liu, J. Mpox Vaccination Hesitancy, Previous Immunisation Coverage, and Vaccination Readiness in the African Region: A Multinational Survey. EClinicalMedicine 2025, 80, 103047. [CrossRef]
[14] Nakoune, E.; Lampaert, E.; Ndjapou, S.G.; Janssens, C.; Zuniga, I.; Van Herp, M.; Fongbia, J.P.; Koyazegbe, T.D.; Selekon, B.; Komoyo, G.F.; et al. A Nosocomial Outbreak of Human Monkeypox in the Central African Republic. Open Forum Infect. Dis. 2017, 4, ofx168. [CrossRef] [PubMed]
[15] Berthet, N.; Nakouné, E.; Whist, E.; Selekon, B.; Burguière, A.M.; Manuguerra, J.C.; Gessain, A.; Kazanji, M. Maculopapular Lesions in the Central African Republic. Lancet 2011, 378, 1354. [CrossRef]
[16] Kalthan, E.; Dondo-Fongbia, J.P.; Yambele, S.; Dieu-Creer, L.R.; Zepio, R.; Pamatika, C.M. Epidémie de 12 Cas de Maladie à Virus Monkeypox dans le District de Bangassou en République Centrafricaine en Décembre 2015. Bull. Soc. Pathol. Exot. 2016, 109, 358–363. [CrossRef] [PubMed]
[17] Page, M.J.; McKenzie, J.E.; Bossuyt, P.M.; Boutron, I.; Hoffmann, T.C.; Mulrow, C.D.; Shamseer, L.; Tetzlaff, J.M.; Akl, E.A.; Brennan, S.E.; et al. The PRISMA 2020 Statement: An Updated Guideline for Reporting Systematic Reviews. BMJ 2021, 372, n71. [CrossRef]
[18] Whitehouse, E.R.; Bonwitt, J.; Hughes, C.M.; Lushima, R.S.; Likafi, T.; Nguete, B.; Kabamba, J.; Monroe, B.; Doty, J.B.; Nakazawa, Y.; et al. Clinical and Epidemiological Findings from Enhanced Monkeypox Surveillance in Tshuapa Province, Democratic Republic of the Congo During 2011–2015. J. Infect. Dis. 2021, 223, 1870–1878. [CrossRef] [PubMed]
[19] Cheuyem, F.Z.L.; Asahngwa, C.; Bakari, W.N.; Achangwa, C.; Goupeyou-Youmsi, J.; Ajong, B.N.; Minkandi, C.A.; Adama, M.; Ndungo, J.H.; Zefack, J.T.; et al. Mpox Clinical Features and Varicella-Zoster Virus Coinfection in the Democratic Republic of Congo: A Systematic Review and Meta-Analysis (1970–2024). medRxiv 2025 preprint. [CrossRef]
[20] Breman, J.G.; Steniowski, M.V.; Zanotto, E.; Gromyko, A.I.; Arita, I. Human Monkeypox, 1970–1979. Bull. World Health Organ. 1980, 58, 165.
[21] Ladnyj, I.D.; Ziegler, P.; Kima, E. A Human Infection Caused by Monkeypox Virus in Basankusu Territory, Democratic Republic of the Congo. Bull. World Health Organ. 1972, 46, 593–597. [PubMed]
[22] Joanna Briggs Institute. Critical Appraisal Tools; The Joanna Briggs Institute: Adelaide, Australia, 2017; Available online: https://jbi.global/critical-appraisal-tools (accessed on 3 December 2024).
[23] Thornhill, J.P.; Barkati, S.; Walmsley, S.; Rockstroh, J.; Antinori, A.; Harrison, L.B.; Palich, R.; Nori, A.; Reeves, I.; Habibi, M.S.; et al. Monkeypox Virus Infection in Humans across 16 Countries—April–June 2022. N. Engl. J. Med. 2022, 387, 679–691. [CrossRef]
[24] Seiffert, S.; Weber, S.; Sack, U.; Keller, T. Use of Logit Transformation within Statistical Analyses of Experimental Results Obtained as Proportions: Example of Method Validation Experiments and EQA in Flow Cytometry. Front. Mol. Biosci. 2024, 11, 1335174. [CrossRef]
[25] R Core Team. R: A Language and Environment for Statistical Computing; R Foundation for Statistical Computing: Vienna, Austria, 2024; Available online: https://www.R-project.org/ (accessed on 19 December 2024).
[26] Kalthan, E.; Tenguere, J.; Ndjapou, S.G.; Koyazengbe, T.A.; Mbomba, J.; Marada, R.M.; Rombebe, P.; Yangueme, P.; Babamingui, M.; Sambella, A.; et al. Investigation of an Outbreak of Monkeypox in an Area Occupied by Armed Groups, Central African Republic. Médecine Mal. Infect. 2018, 48, 263–268. [CrossRef]
[27] Besombes, C.; Gonofio, E.; Konamna, X.; Selekon, B.; Gessain, A.; Berthet, N.; Manuguerra, J.C.; Fontanet, A.; Nakouné, E. Intrafamily Transmission of Monkeypox Virus, Central African Republic, 2018. Emerg. Infect. Dis. 2019, 25, 1602–1604. [CrossRef]
[28] Durski, K.N.; McCollum, A.M.; Nakazawa, Y.; Petersen, B.W.; Reynolds, M.G.; Briand, S.; Djingarey, M.H.; Olson, V.; Damon, I.K.; Khalakdina, A. Emergence of Monkeypox—West and Central Africa, 1970–2017. MMWR Morb. Mortal. Wkly. Rep. 2018, 16, 306–310. [CrossRef] [PubMed]
[29] Tarín-Vicente, E.J.; Alemany, A.; Agud-Dios, M.; Ubals, M.; Suñer, C.; Antón, A.; Arando, M.; Arroyo-Andrés, J.; Calderón-Lozano, L.; Casañ, C.; et al. Clinical Presentation and Virological Assessment of Confirmed Human Monkeypox Virus Cases in Spain: A Prospective Observational Cohort Study. Lancet 2022, 400, 661–669. [CrossRef]
[30] Reynolds, M.G.; Yorita, K.L.; Kuehnert, M.J.; Davidson, W.B.; Huhn, G.D.; Holman, R.C.; Damon, I.K. Clinical Manifestations of Human Monkeypox Influenced by Route of Infection. J. Infect. Dis. 2006, 194, 773–780. [CrossRef]
[31] Rimoin, A.W.; Mulembakani, P.M.; Johnston, S.C.; Smith, J.L.; Kisalu, N.K.; Kinkela, T.L.; Blumberg, S.; Thomassen, H.A.; Pike, B.L.; Fair, J.N.; et al. Major Increase in Human Monkeypox Incidence 30 Years after Smallpox Vaccination Campaigns Cease in the Democratic Republic of Congo. Proc. Natl. Acad. Sci. USA 2010, 107, 16262–16267. [CrossRef] [PubMed]
[32] Jezek, Z.; Grab, B.; Szczeniowski, M.; Paluku, K.M.; Mutombo, M. Clinico-Epidemiological Features of Monkeypox Patients with an Animal or Human Source of Infection. Bull. World Health Organ. 1988, 66, 459–464.
[33] Lango, H.O.; Benjendo, L.M.D.H.; Biallé, B.; Gbazi, S.; Mapoka, E.; Pounguiza, S.; Bobossi, C.; N’Yetobouko, S.; Baguida-Bokia, C.; Heredeibona, M.; et al. Epidemiological and Clinical Profile of Mpox Diagnosed at the National Laboratory of Clinical Biology of Public Health in Bangui, Central African Republic. Health 2025, 17, 1408–1416. [CrossRef]
[34] Malaka, C.N.; Patrono, L.V.; Tombolomako, T.B.; Farra, E.; Sibiro, O.; Garba-Ouangolé, S.; Selekon, B.; Lemon, C.G.; Mbrenga, F.; Soumah, A.; et al. Genomic Epidemiology of Clade Ia Monkeypox Viruses Circulating in the Central African Republic in 2022-24: A Retrospective Cross-Sectional Study. Lancet Microbe 2025, 6, 101173. [CrossRef]
[35] OCHA. Central African Republic: Humanitarian Needs and Response Plan. Available online: https://www.unocha.org/publications/report/central-african-republic/central-african-republic-humanitarian-needs-and-response-plan-december-2024 (accessed on 7 July 2025).
[36] MSF Eastern Africa. Doctors Without Borders. Central African Republic: Repeated Attacks on Medical Care Leave People Vulnerable to Disease and Death. Available online: https://msf.or.ke/news-and-resources/latest-news/central-african-republic-repeated-attacks-medical-care-leave-people (accessed on 7 July 2025).
[37] Doty, J.B.; Malekani, J.M.; Kalemba, L.N.; Stanley, W.T.; Monroe, B.P.; Nakazawa, Y.U.; Mauldin, M.R.; Bakambana, T.L.; Liyandja Dja Liyandja, T.; Braden, Z.H.; et al. Assessing Monkeypox Virus Prevalence in Small Mammals at the Human–Animal Interface in the Democratic Republic of the Congo. Viruses 2017, 9, 283. [CrossRef]
[38] WHO. Mpox. Available online: https://www.who.int/news-room/fact-sheets/detail/mpox (accessed on 2 July 2025).
[39] Cheuyem, F.Z.L.; Zombré, D.; Banthas-Bata, G.G.; Lalani, A.; Yaman, A.; Romano, S.; Mbanga, C.; Andinwoh, N.B.; Mokom, S.B.; Saidu, Y. Using a Multi-Criteria Method for the Recruitment and Deployment of Health Human Resources to Strengthen the Health System in Central African Republic. Res. Sq. 2024 preprint. [CrossRef]
[40] Beer, E.M.; Rao, V.B. A Systematic Review of the Epidemiology of Human Monkeypox Outbreaks and Implications for Outbreak Strategy. PLoS Negl. Trop. Dis. 2019, 13, e0007791. [CrossRef]
[41] Philpott, D.; Hughes, C.M.; Alroy, K.A.; Kerins, J.L.; Pavlick, J.; Asbel, L.; Crawley, A.; Newman, A.P.; Spencer, H.; Feldpausch, A.; et al. Epidemiologic and Clinical Characteristics of Monkeypox Cases—United States, May 17-July 22, 2022. MMWR Morb. Mortal. Wkly. Rep. 2022, 71, 1018–1022. [CrossRef] [PubMed]
[42] Fine, P.E.; Jezek, Z.; Grab, B.; Dixon, H. The Transmission Potential of Monkeypox Virus in Human Populations. Int. J. Epidemiol. 1988, 17, 643–650. [CrossRef] [PubMed]
[43] Nguyen, P.Y.; Ajisegiri, W.S.; Costantino, V.; Chughtai, A.A.; MacIntyre, C.R. Reemergence of Human Monkeypox and Declining Population Immunity in the Context of Urbanization, Nigeria, 2017–2020. Emerg. Infect. Dis. 2021, 27, 1007–1014. [CrossRef] [PubMed]
[44] CDC. Interim Clinical Considerations for Use of Vaccine for Mpox Prevention in the United States. Mpox. 2025. Available online: https://www.cdc.gov/mpox/hcp/vaccine-considerations/vaccination-overview.html (accessed on 2 July 2025).
[45] GOV.UK. Mpox: Background Information. Available online: https://www.gov.uk/guidance/monkeypox (accessed on 2 July 2025).
Disclaimer/Publisher’s Note: The views expressed in this article are those of the author(s) and do not necessarily reflect the views of the publisher or editors. The publisher and editors assume no responsibility for any injury or damage resulting from the use of information contained herein.
©2026 Copyright by the Authors.
Licensed as an open-access article distributed under the terms and conditions of the CC BY 4.0 license